
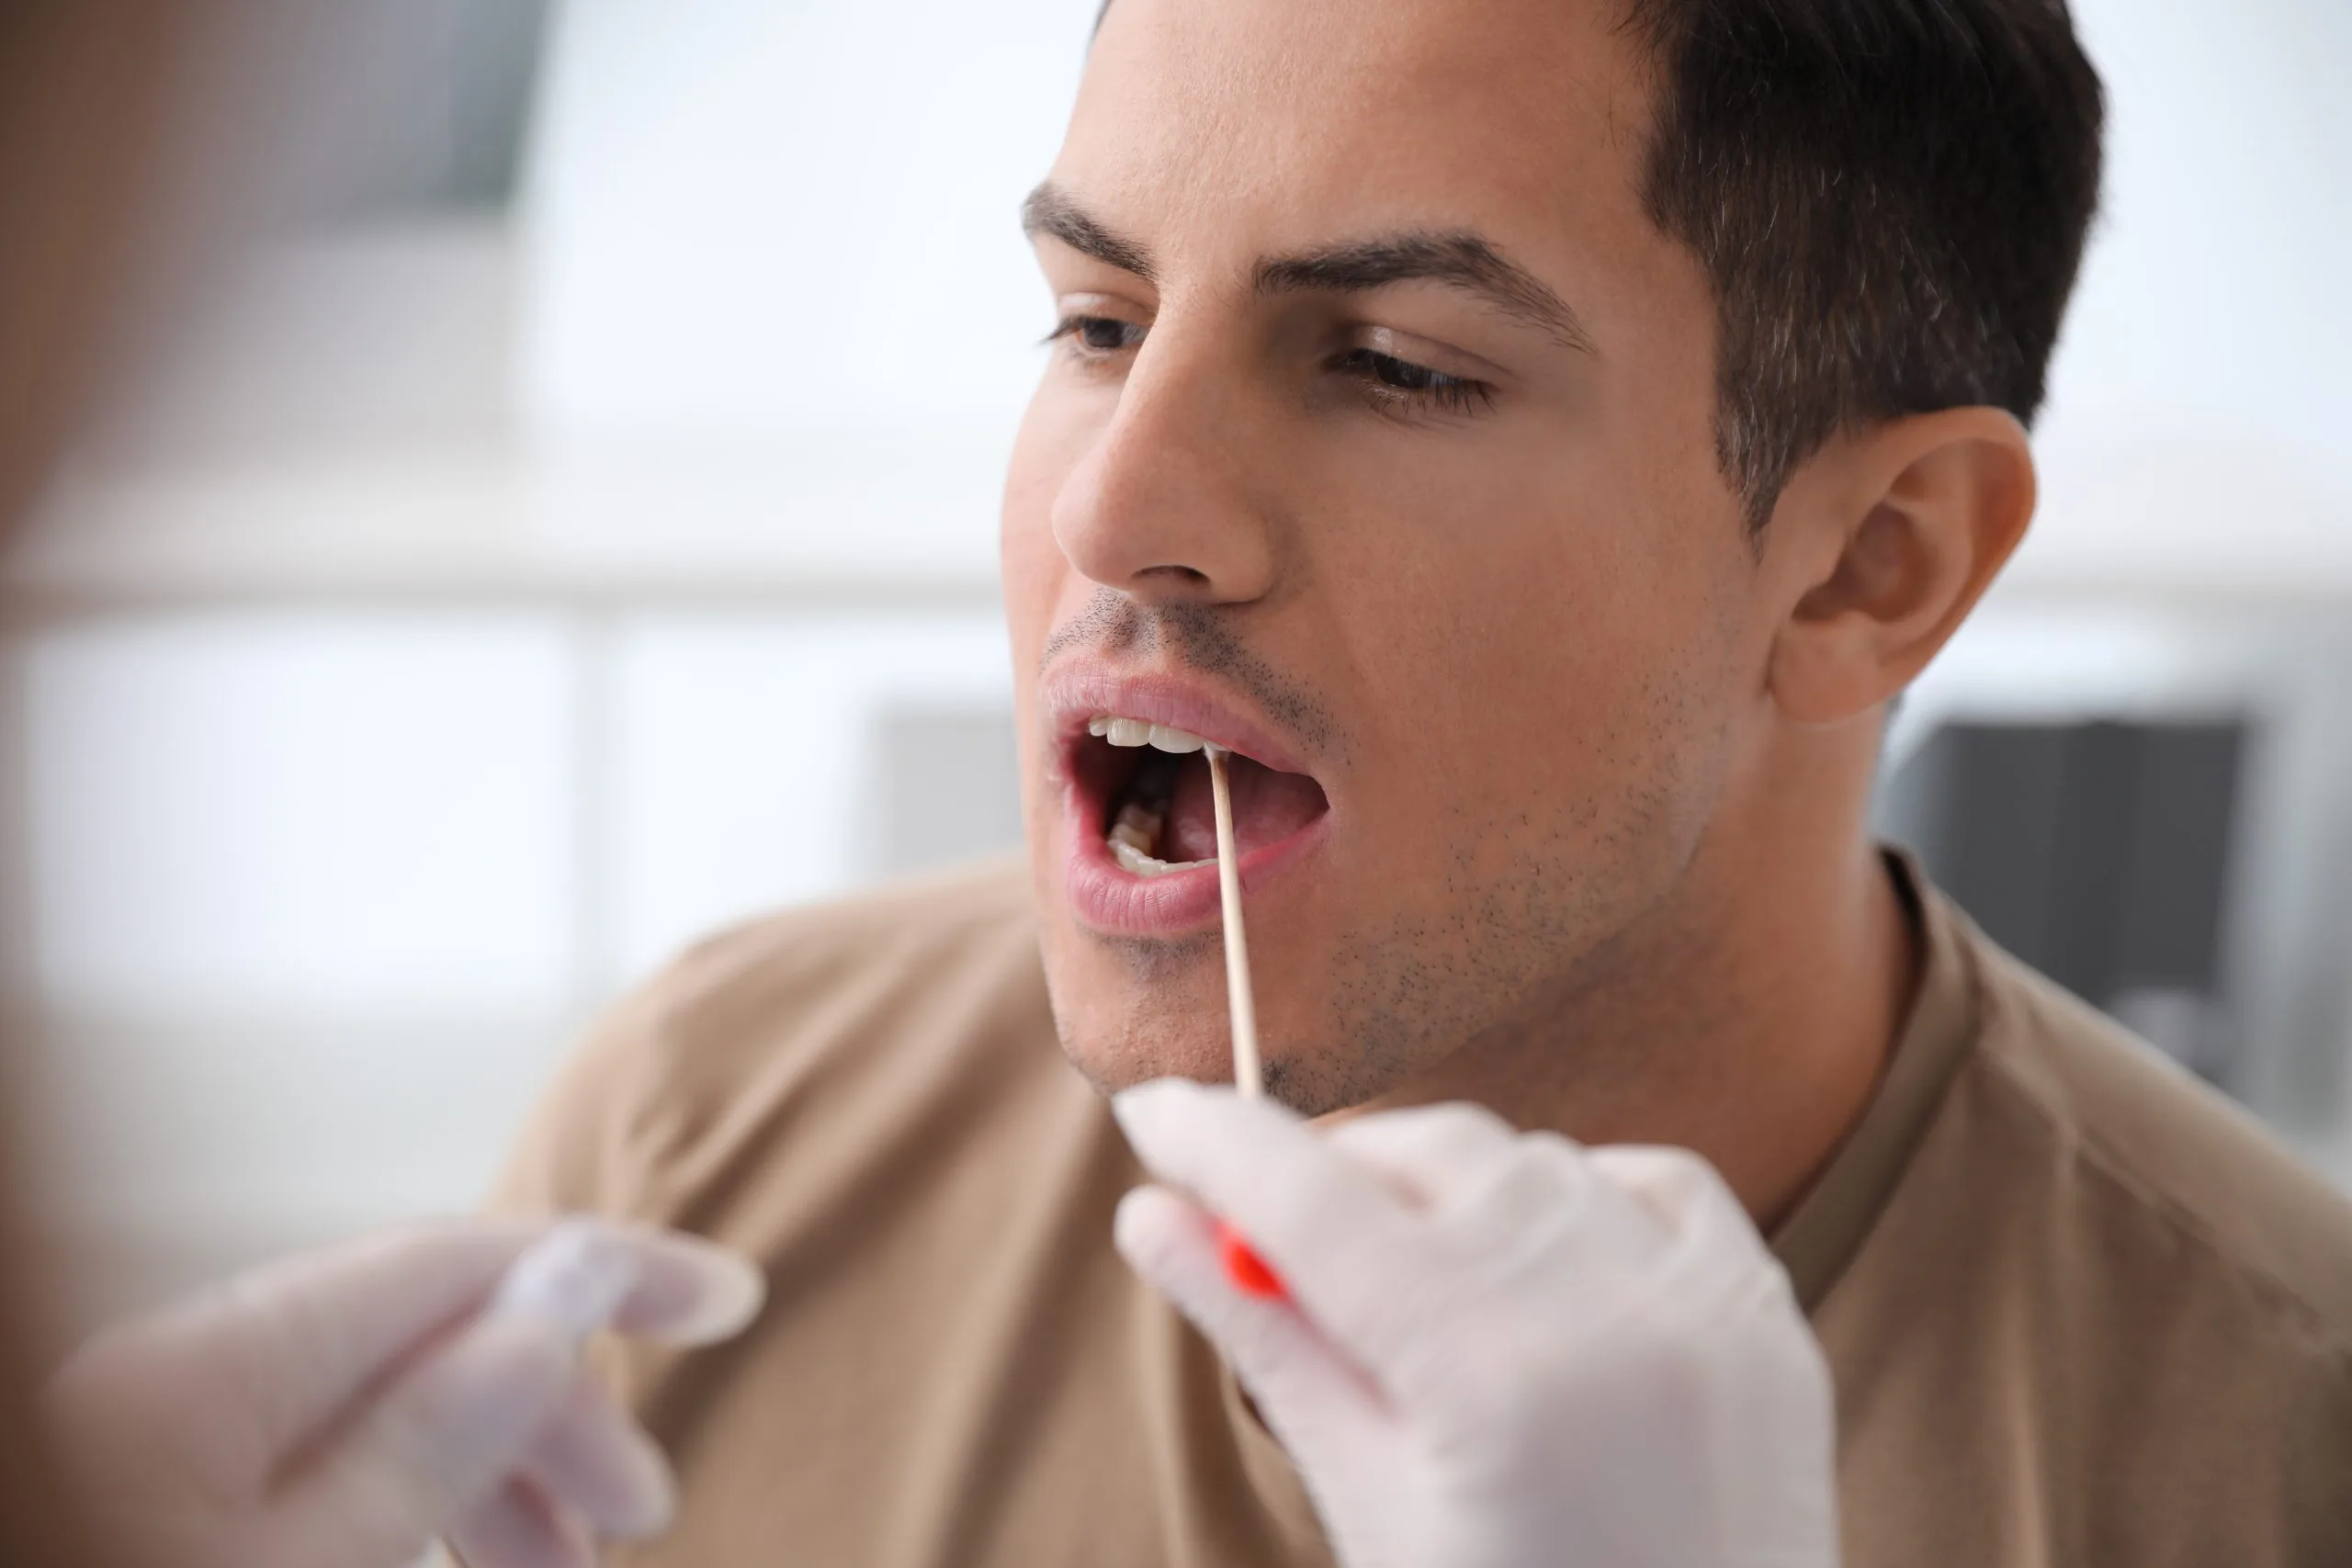
Genetic testing for psychiatric medication analyzes small differences in your DNA to help predict how your body may process and respond to psychiatric drugs. This tool offers a biological snapshot of enzymes, receptors, and related pathways – not a substitute for clinical judgment. It is used alongside a full psychiatric evaluation and ongoing medication management at our practice in Surprise, AZ, to make care more targeted and less of a guessing game.
This article covers:
The science and steps of a typical test
The genes and medicines that show up on reports
Who may gain the most from testing
What results can and cannot tell you
Genetic testing for psychiatric medication, also known as pharmacogenomic (PGx) testing, studies parts of your DNA related to how medicines are absorbed, broken down, and used in the brain. Your genes are stable, so a one-time sample can keep informing care for years. The test does not diagnose depression, anxiety, ADHD, bipolar disorder, or any other condition, and it does not replace a conversation about symptoms, sleep, trauma history, other health problems, or past reactions to medicine.
Psychiatric diagnosis is based on symptoms, history, and clinical evaluation.
Genetic testing asks a narrower question: given this person’s genes, how might this class of medicine behave in their body?
You are not sending a sample so a lab can tell you “what is wrong with you.” You are sending a sample so a lab can flag gene-drug pairs that may need extra caution, a different dose, or a different first choice.
Alpha Health and Wellness offers genetic testing as part of a broader mental health practice. Stephanie Dockins is a dual board-certified provider and brings experience from inpatient crisis work, outpatient care for people with serious mental illness, correctional settings, and private practice.
Four pieces explain how genetic testing for psychiatric medication works in daily practice: the science of how genes affect drugs, the sample-and-report process, the lab methods that read your DNA, and the scoring systems that turn raw results into a readable report.
The core science of pharmacogenomics focuses on enzymes, primarily a group in the liver called the cytochrome P450 (CYP450) system. After you take a dose, the drug is absorbed, carried through the blood, broken down or activated by enzymes, moved into tissues (including the brain) by transporters, bound to receptors or other targets, and cleared from the body. Genes help build the proteins that run those steps, and a small spelling change – called a variant or polymorphism – can make an enzyme work faster, slower, or not at all.
Based on your genetics, you might be classified as:
Poor metabolizer: Little or no enzyme activity.
Intermediate metabolizer: Reduced activity. A cautious dose or a different drug may be considered.
Normal (extensive) metabolizer: Typical activity. Many standard dosing plans assume this pattern.
Rapid or ultrarapid metabolizer: Extra activity. The drug may be cleared too quickly to help.
Not every gene uses this exact language. Pharmacodynamic genes affect receptors rather than metabolism and speak more to how a drug might “land” in the brain than to how fast it is cleared.
Environment still matters: smoking can speed up certain enzymes; other prescriptions, supplements, and even some foods can slow them down; age, liver and kidney function, pregnancy, inflammation, and other medical conditions change how drugs behave. Genes are one piece of a larger puzzle.
The process for patients at Alpha Health and Wellness is straightforward and non-invasive. You do not need to fast or stay in a hospital. The sample is typically saliva or a cheek swab; in some cases, a blood sample is used. However, many psychiatric panels rely on a swab because it is simple to collect in a clinic or at home with clear instructions.
A typical sequence looks like this:
Consultation: You and your provider decide if testing could add useful information. Our team determines if genetic testing is appropriate based on your symptoms, treatment history, and overall health.
Sample collection: You receive a collection kit and swab the inside of your cheek or provide saliva, following directions so the sample is not contaminated. This is done quickly and painlessly.
Lab analysis: The sample is labeled and sent to a specialized laboratory that runs a psychiatric pharmacogenomic panel. The lab reads selected gene regions – not your entire genome.
Report and review: Software and clinical rules convert results into a report. Our team reviews it with you during a follow-up appointment and places it next to your symptom history, past medication trials, other lab work, and medication management goals.
Turnaround time varies by lab, but many patients wait from several days to one to two weeks. The DNA itself does not expire the way a blood sugar reading does. Once you have a valid result, it can stay in your chart and inform later decisions, including a new medicine considered years from now.
The labs we partner with use advanced technology like genotyping arrays to analyze your DNA sample. Genotyping checks specific known spots in selected genes rather than reading every letter of your DNA – think of it as checking certain pages in a book rather than copying the whole library. Those pages were chosen because research has linked them to drug metabolism or drug response. The process is highly accurate and focuses only on the genes known to influence drug response, not your entire genome.
Common lab techniques include:
PCR (polymerase chain reaction) to make many copies of the DNA regions of interest
Microarray chips or similar platforms that detect known variants (single-nucleotide polymorphisms, or SNPs) at many sites at once
In some cases, next-generation sequencing for broader coverage of selected genes
Quality controls confirm that the sample has enough DNA, that the signals are clear, and that results can be interpreted. Reports usually list the genes tested, the variants found, and the predicted function (for example, CYP2D6 poor metabolizer).
What the technology does not do:
It does not scan for every possible rare mutation
It does not predict your future mental health
It does not measure current drug levels in your blood (that is a different test)
Because panels differ, two labs may not list identical genes or identical drug categories. Results should be reviewed by the provider who ordered the test and who knows which panel was used.
Once your genetic variations are identified, the lab uses a sophisticated algorithm to interpret the data. This algorithm cross-references your genetic profile against published gene-drug research, FDA labeling notes, and expert consensus groups, then translates the information into a clear, actionable report.
The output is usually a color-coded or category-coded list of medicines:
Green-style categories often mean no gene-based caution was found for that drug
Yellow-style categories often mean a dose change, extra monitoring, or moderate caution
Red-style categories often mean a significant gene-drug interaction was flagged
A “caution” flag is not a ban. A “use as directed” flag is not a guarantee that the drug will work. Evidence is stronger for some gene-drug pairs (for example, certain CYP enzymes and dose) than for others (for example, some receptor genes and antidepressant response). The algorithm also cannot see whether you take the medicine every day, whether another drug is blocking the same enzyme, whether symptoms are driven more by untreated sleep problems, substance use, or medical illness, or whether a past “failure” was actually a dose that was too low or a trial that was too short. The report is a map. Your provider still has to drive.
The test focuses on two main types of genes that influence your response to medication: pharmacokinetic genes (how the body handles the drug) and pharmacodynamic genes (how the drug may act on the body).
These genes primarily affect how your body acts on a drug – how it is absorbed, distributed, metabolized, and ultimately cleared. The cytochrome P450 family, often shortened to CYP, is the group you will see most often.
Genes commonly analyzed include:
CYP2D6: Helps metabolize many antidepressants (SSRIs and tricyclics), some antipsychotics, and some ADHD medicines. Poor metabolizers may need lower doses. Ultrarapid metabolizers may clear some medicines so quickly that standard doses never reach a helpful level. CYP2D6 is also involved in turning some medicines from an inactive form into an active form, which can flip the usual logic.
CYP2C19: Affects several common antidepressants, anti-anxiety medications, and some other psychiatric medicines. For some drugs, FDA labeling already comments on CYP2C19 status and dosing.
CYP2C9, CYP1A2, CYP3A4, and CYP3A5: Appear on many panels. CYP3A4/CYP3A5 metabolize a very large percentage of all medications, including many used in psychiatry. CYP1A2 is notable because smoking can induce it, meaning a person who smokes may process some medicines faster than the gene result alone would suggest.
UGT genes and other non-CYP enzymes: May appear for medicines that follow different clearance paths.
Transporter genes, such as ABCB1 (sometimes called MDR1): Relate to how drugs cross membranes, including at the blood-brain barrier. Evidence for some transporters is still developing, so providers weigh those findings with more caution than well-established CYP results.
When you sit down with a report, pharmacokinetic genes often translate into practical dose questions: start lower, avoid this drug, or do not be surprised if a usual dose does nothing.
These genes influence how a drug acts on your body at a cellular level. They can affect how well a medication binds to its target (like a brain cell receptor) or how it influences brain signaling pathways.
Examples include:
SLC6A4: The serotonin transporter gene that many SSRI antidepressants act on. Some studies have looked at a promoter variant (often called 5-HTTLPR) and antidepressant response or side-effect burden. Findings are mixed across populations, so this gene is usually treated as supportive information rather than a yes-or-no rule.
HTR2A and related serotonin receptor genes: Studied for links to treatment response and to side effects, such as movement symptoms or sexual side effects with certain drugs. The signal is not as strong as for many CYP genes.
COMT: Involved in breaking down neurotransmitters like dopamine in the prefrontal cortex. Variants are sometimes discussed in the context of ADHD medicines, working memory, and stress response. They do not diagnose ADHD, and they do not pick a stimulant by themselves.
BDNF (brain-derived neurotrophic factor) and other signaling genes: Appear on some panels. Research is ongoing. Many providers treat these as lower-weight findings.
ADRA2A: Relates to a norepinephrine receptor and is sometimes discussed with ADHD treatment response.
Pharmacodynamic results often feel more abstract than metabolizer status. They may nudge a conversation rather than dictate a dose.
The reports cover a broad spectrum of medications used to treat mental health conditions. Exact lists depend on the lab, but you can expect to see many of the names that come up in everyday mental health care.
Classes typically included:
Antidepressants (SSRIs, SNRIs, TCAs, and some atypical agents)
Antipsychotics, which may be used for schizophrenia, psychosis, bipolar disorder, or as an add-on treatment in some depression cases
Anxiolytics (anti-anxiety medications) and some sleep-related medicines, which matter for people whose main struggle is insomnia.
Deciding to undergo genetic testing is a personal choice made in collaboration with your provider. Our team does not require a gene panel to begin a 60-minute evaluation or to receive medication follow-up. Testing is offered because it can add insight, not because it is the only path to help.
Useful points to cover with your provider include:
What decision will this change? If the next prescription is already clear and you have tolerated similar medicines, testing may wait. If you are staring at a long list of past failures, testing may be timely.
What panel is being used? Ask which genes are included and whether the lab’s report is designed for psychiatric medicines.
How will results be explained? Plan a follow-up to review the report rather than reading colors on your own.
What remains uncertain? Receptor-gene findings, mixed research on antidepressant prediction, and the role of life stress should be named out loud.
Privacy: Genetic data is health information. It belongs in your medical record with the same protections as other clinical data.
Understanding how genetic testing for psychiatric medication works reveals its potential to transform mental healthcare. By providing a window into your unique genetic makeup, it allows for a more precise, personalized, and proactive approach – moving care away from trial and error and toward informed, collaborative decision-making. Genetic testing will keep improving as research ties more gene-drug pairs to real outcomes and as reports become clearer about evidence strength.

About the Author
Stephanie Dockins, PMHNP-BC, FNP-C
Take the First Step Toward a More Balanced & Fulfilling Life
September 10, 2026
Explore More Blogs
Our team is here to provide the expert guidance and compassionate support you deserve.